
Ipas DRC
Non-profit organization


At just 16 years old, Buzima’s life changed dramatically after experiencing sexual violence that resulted in an early pregnancy. Overnight, she was forced to leave school and faced stigma, rejection and significant social and economic challenges. Without support, she raised her child on her own while carrying the burden of the hardships she endured during adolescence. For years, one question stayed with her : What if my daughter faced the same fate?
As her daughter grew older, memories of her own adolescence never felt far away. Buzima often found herself wondering whether her daughter might face the same challenges that had altered the course of her own life. Determined to help her build a different future, she decided to share her story and the lessons she had learned.

For Buzima, the visit meant far more than access to a health service. It was reassurance that her daughter would have opportunities she never had—the chance to stay in school and build the future she chooses.
Buzima’s story is deeply personal, but the challenges she faced are shared by many girls across Burundi.
Like Buzima, thousands of adolescent girls face barriers that can limit their health, education and future opportunities. Early pregnancy remains a significant challenge, particularly for girls who lack access to accurate information and youth-friendly health services.
National data highlight the scale of the issue. According to the Demographic and Health Survey (DHS), Burundian women have their first sexual experience at an average age of 19.6 years—more than three years earlier than men. Nearly one in four women marry before the age of 18, a rate eight times higher than that of men. Among women aged 15–49 who are not in union, 34 percent use a modern contraceptive method, while 6 percent are already mothers and 2 percent are pregnant at the time of the survey.
Behind these numbers are stories of girls whose education, aspirations and opportunities are often interrupted too soon.
The impact on education is particularly significant. According to the 2023 Final Report on Pregnancy in School Settings, more than 2,000 girls leave school each year because of pregnancy. During the 2022–2023 academic year alone, 879 students dropped out for this reason. For many girls, pregnancy can mean not only leaving school, but also facing long-term social and economic consequences.
When adolescent girls have access to accurate information, supportive adults and quality sexual and reproductive health services, they are better equipped to make informed decisions about their health and future.
To help make this possible, Burundi’s National Reproductive Health Program (PNSR), with support from Ipas Burundi, is strengthening the capacity of health facilities and providers to deliver respectful, rights-based and youth-friendly care. Through supportive supervision, mentoring and ongoing technical assistance, providers are better prepared to meet the needs of women and adolescent girls.
At Gikomero Health Center, that investment made all the difference for Buzima and her daughter. After being turned away during an earlier visit, her daughter found a very different experience—one built on respect, information and support.

Today, Buzima shares her experience with other parents in her community. Drawing on her own journey, she encourages them to talk openly with their children, listen without judgment and help them access the information and services they need.
For her, protecting adolescent girls often begins at home—with honest conversations, trust and support. But those conversations must be backed by health services that are accessible, respectful and responsive to young people’s needs.

For Buzima, that change is already visible. What began as a mother’s determination to protect her daughter has become a source of hope for other families in her community—and a reminder of what is possible when girls can access accurate information, supportive adults and quality sexual and reproductive health services.


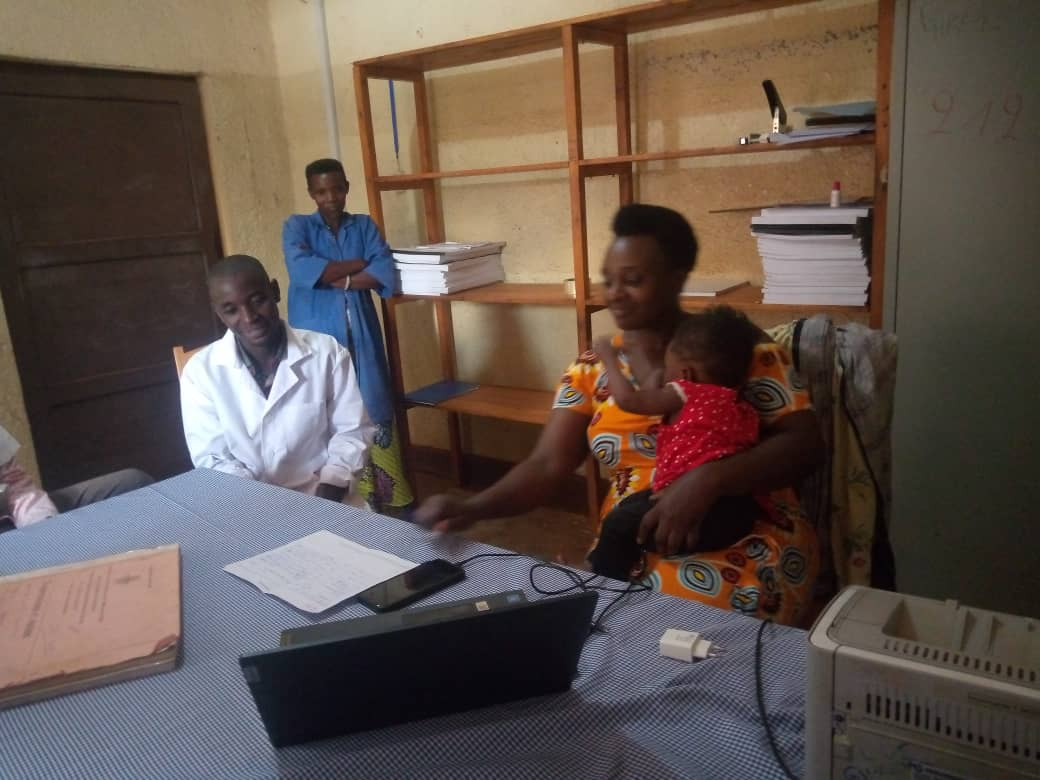

Married for several years and raising several children, Sifa and Amisi face many of the same challenges experienced by families throughout their community. Like many couples, they wanted to better plan their family’s future and avoid closely spaced pregnancies, but they did not always have access to reliable information that would allow them to make informed decisions.
“Before, I did not space my pregnancies. Some of my friends told me about medicines that could be used for family planning. Because these methods were not available free of charge at the health facility, I went to a pharmacy to buy a method that I took every day. I wanted to avoid closely spaced pregnancies, but I did not know enough about the different contraceptive methods.”

Like many others in their community, the couple was exposed to rumors and conflicting information about family planning. Conversations about birth spacing were rarely held openly, even though closely spaced pregnancies can affect women’s health, children’s well-being, and a household’s ability to meet essential needs.

Everything began to change when they heard about a community learning laboratory organized in their neighborhood by YARH-DRC (Youth Alliance for Reproductive Health), a youth-led organization and member of the YouthSprint Coalition that works to advance sexual and reproductive health and rights. Implemented with technical and financial support from Ipas DRC as part of a project funded by Global Affairs Canada, the laboratory offered community members a space to identify challenges affecting their daily lives, share experiences, and work together to develop solutions grounded in their realities.
Unlike a traditional awareness-raising session, the laboratory placed participants at the center of the process. Together, community members identified challenges facing families, analyzed their root causes, and explored practical solutions that could be tested within their own communities. In Kiziba, discussions highlighted concerns about closely spaced pregnancies, limited access to reliable contraceptive information, and persistent myths about family planning methods.

“When I learned that there was a space where people could openly discuss sexual and reproductive health issues, I became interested and joined the discussions. What I learned helped me better understand the different contraceptive methods, why they matter, and how they are used.”
Throughout the sessions, couples had the opportunity to ask questions, explore available options, and reflect together on what would work best for their families. The decisions remained entirely voluntary: some couples chose a fertility awareness method using a cycle bead necklace, while others opted for a modern contraceptive method.
More importantly, the discussions helped open dialogue within households.
Couples began talking more openly about their needs, family goals, and decisions related to birth spacing. Home visits and individualized support provided by YARH-DRC reinforced these conversations, allowing partners to continue reflecting together long after the community sessions had ended.
“Today, I better understand the different methods. I also realized that I can share this information with other people around me. Recently, I have been sharing what I learned.”
Sifa and Amisi’s story is not unique. Two community learning laboratories supported four couples facing challenges related to closely spaced pregnancies and economic violence within households. While the issues differed, a common lesson emerged: when families have safe spaces to discuss their concerns, they are better equipped to identify solutions, make informed choices, and act together.
The experience also demonstrated the power of community-led change. By creating spaces for dialogue, learning, and collective problem-solving, the laboratories enabled participants to challenge misconceptions and develop solutions that reflected their own priorities and realities.
“The community learning laboratories created a space where community members could speak freely, share experiences, and work together to find solutions to the challenges affecting them.”


For many adolescent girls, understanding their bodies, knowing their rights and accessing reliable sexual and reproductive health information is already a challenge. During the Ebola outbreak in Beni, that challenge became even greater for girls living with disabilities, who often faced additional barriers to accessing the information they needed to protect their health and well-being.
In eastern Democratic Republic of the Congo, Agnes is part of a generation of young people growing up amid overlapping public health and humanitarian crises. Like many girls with hearing impairments, she often felt left out. While much of the public attention was focused on the Ebola response, adolescent girls’ sexual and reproductive health needs did not disappear.
Information about menstrual health, personal hygiene, protection from violence and sexual and reproductive health services was not always available in formats that were accessible to her. Agnes knew that this information existed, but accessing and understanding it was not always easy.

That began to change when she participated in an activity organized by Youth Alliance for Reproductive Health with support from Ipas DRC through WISH2, a programme funded by the UK government through the Foreign, Commonwealth and Development Office (FCDO). At a time when the Ebola outbreak was disrupting access to information and essential services across communities, the initiative aimed to ensure that adolescent girls living with disabilities were not left behind.
During the session, participants discussed menstrual health, personal hygiene and protection from violence. Through practical demonstrations and approaches tailored to their needs, Agnes was able to actively engage, ask questions and better understand topics that are often surrounded by silence and stigma.
For Agnes, the most significant outcome was not simply the information she received. It was the feeling of finally being seen.
“Today, I feel heard, valued and included. I know that I, too, have the right to information, care and protection. To me, that is what inclusion means: ensuring that no one is left behind, especially when it comes to our health and dignity.”

Her story highlights an often-overlooked reality: access to information is a prerequisite for the power to choose. When adolescent girls cannot access information that is adapted to their age, circumstances or abilities, they face greater risks of unintended pregnancy, violence and exclusion from essential health services.
According to Christelle Ambiti, focal point for YARH-DRC in Beni, girls with hearing impairments continue to face significant challenges in accessing sexual and reproductive health information and services. In a context marked by the Ebola outbreak, unequal access to information and heightened vulnerability to violence, information itself becomes a critical form of protection.
She notes that five girls left school because of early and unintended pregnancies in the previous year alone. Behind those numbers are interrupted dreams, lost opportunities and young lives shaped by barriers to information and services.
For frontline teams, the solution goes beyond making services available. Information must also be accessible, understandable and responsive to the realities of every girl so that she can make informed decisions about her health and future.

Agnes’ story shows that inclusion often begins with something simple: making information accessible. Even during a public health emergency, adolescent girls’ sexual and reproductive health needs do not disappear. On the contrary, ensuring equitable access to information becomes even more important so that every girl can protect her health, stay in school and make informed decisions about her future.

How the Makoki ya Mwasi project advances women’s sexual and reproductive rights in humanitarian settings.
At 32, Amani (name changed) is a mother of five living in the Alpha displacement camp in Beni, North Kivu. Like thousands of families forced to flee violence in eastern Democratic Republic of Congo, her life is shaped by uncertainty, limited resources, and the daily challenge of keeping her children safe and healthy.
“Life in the camp is extremely hard. Some days, I don’t know what my children will eat tomorrow. Every day is about survival,”
she explains.
In a context where access to basic services is fragile and daily survival takes priority, the prospect of another pregnancy became a source of deep concern. With food scarce and health services difficult to access, Amani questioned how she could protect her own health while continuing to care for her children. In displacement, decisions about one’s body are too often shaped by circumstance rather than by choice.

A turning point came when Amani connected with the Mashujaa — a community‑based network supporting women and girls with information, accompaniment, and referrals on sexual and reproductive health and rights.
Through open, respectful dialogue, she learned that access to family planning is a right — not a privilege limited to stable settings. She began to see it as essential to her health, her autonomy, and her family’s well‑being, especially in situations of displacement and crisis.
With accurate information and supportive guidance, Amani felt empowered to seek care.
Amani visited the Butsili Health Center, where health providers had received capacity‑strengthening support from the Ministry of Health, in collaboration with Ipas DRC. She received care grounded in respect, confidentiality, and informed choice. Together with the provider, she discussed options and selected a family planning method aligned with her needs and decisions.
“I feel relieved,” she says. “I can care for my children without constantly fearing another pregnancy while we are already struggling.”
For Amani, this access went far beyond clinical service. It represented a step toward reclaiming control over her body and her future in a context where so much felt uncertain. With her health needs addressed, she can now focus on what matters most: caring for her children and moving forward with greater peace of mind.
Amani’s experience reflects the broader impact sought by Ipas DRC, whose work focuses on addressing inequities in access to sexual and reproductive health care across the Democratic Republic of Congo — particularly for women and girls living in crisis‑affected and highly vulnerable settings.
This work is part of the Makoki ya Mwasi project, implemented by Ipas DRC with support from the Swedish International Development Cooperation Agency (Sida). The project aims to ensure that women and girls — including those living in the most fragile and humanitarian contexts — can access reliable information and high‑quality sexual and reproductive health services. It also contributes to reducing gender‑based violence and unintended pregnancies by placing women’s rights, choices, and dignity at the center of all interventions.
Implemented in North and South Kivu, Kasaï, and Kinshasa, the project takes a comprehensive approach by:
Through this integrated approach, thousands of women and girls have been supported to make informed decisions about their sexual and reproductive health, with meaningful changes observed at both individual and community levels.
In the Alpha displacement camp — as in many crisis‑affected communities across eastern DRC — Ipas DRC demonstrates that rights‑based sexual and reproductive health care is both possible and essential, even in contexts of instability and emergency.
For Amani, this support has meant one clear and powerful outcome: the ability to decide about her own body, despite displacement and hardship. A decision that allows her to look ahead with renewed confidence — for herself and her children.

In the Democratic Republic of Congo, motherhood is often celebrated as a blessing. Yet for many women, an unintended pregnancy can quickly become a source of fear and isolation—especially when a partner withdraws responsibility and support. In these moments, women are left to navigate not only social pressure and economic uncertainty, but deeply personal decisions about their bodies and futures.
These challenges are compounded by persistent gaps in access to contraception and sexual and reproductive health care national data reflects this reality :
only 10.9% of women in union use modern contraceptive methods (DHS 2023–2024). Even more concerning, 32% of married or in‑union women who wish to space or limit births are unable to access their preferred family planning methods,. and in 2024, just 21% of family planning demand was met. For many women, this means facing unintended pregnancies without the information, services, or support needed to make informed choices.
At 26, Matondo (name changed) is already a mother to a young daughter. When she became pregnant again, she did not realize it immediately. With an irregular menstrual cycle, the signs were unclear.

“My cycle is irregular, and if I said I know how to calculate it, I would be lying—I don’t,”
she explains.
When she eventually learned she was pregnant, the shock was compounded by her partner’s response: he refused to acknowledge the pregnancy and left her to face the situation alone. With no stable income, no independent housing, and no support from the child’s father, Matondo felt overwhelmed by the weight of expectations placed on her. Unsure of what to do, and struggling emotionally, she decided to seek help at the Center of Excellence within the Kintambo Maternity—one of the facilities supported by Ipas DRC.
“I had so many thoughts about this pregnancy,” she recalls. “I kept asking myself whether I would be able to care for another child, especially since I was living with my aunt. I felt lost. That’s when I decided to go to the Center of Excellence at the Kintambo Maternity.”
Until recently many women in the DRC had no access to safe, regulated abortion care. This forced countless women into unsafe and clandestine practices, with devastating consequences for their health and lives.
The country’s accession to the Maputo Protocol in 2018 marked a critical turning point. The protocol affirms women’s rights to sexual and reproductive health, including access to safe abortion under specific circumstances such as rape, incest, or risks to a woman’s physical or mental health. While legal reform alone is not enough, it provides an essential foundation for rights‑based care.
When Matondo arrived at the health facility, it was clear that her emotional state required as much attention as her physical health.
“She was deeply distressed,” explains Aimée Olenga, the midwife who accompanied her.. “She felt trapped, unable to cope with the situation she was facing. At one point, she told me she saw only two options—having an abortion or ending her own life.”

Through patient listening, counseling, and respectful care, Matondo was supported through a safe abortion process that prioritized her dignity, well‑being, and choices. Afterward, she described feeling calmer and relieved—for the first time able to think clearly about her future. Psychological support, Aimée emphasizes, is not optional. It is a core part of care—helping women rebuild confidence, reclaim agency, and move forward without fear or shame.
Matondo’s experience highlights how access to respectful, rights‑based care depends on a strong and well‑structured health system.
Ipas DRC works to build a sustainable abortion ecosystem that enables women to fully exercise their sexual and reproductive health and rights. To do so, the organization supports the delivery of comprehensive, woman‑centered abortion care (CAC) by strengthening the health system, particularly the capacity of health care providers.
Active listening, emotional support, and respectful counseling are part of the rights‑based and quality‑of‑care approach promoted by Ipas, which guides how services are delivered. Family planning remains a core component of the broader sexual and reproductive health and rights continuum.
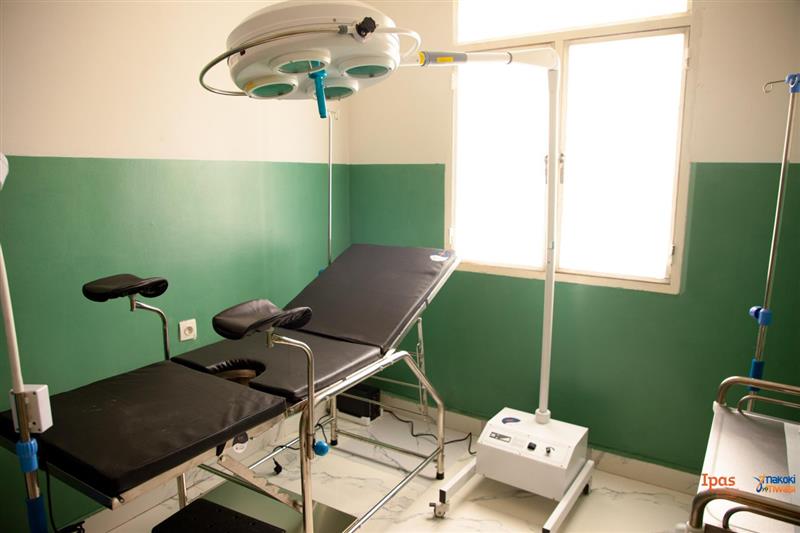

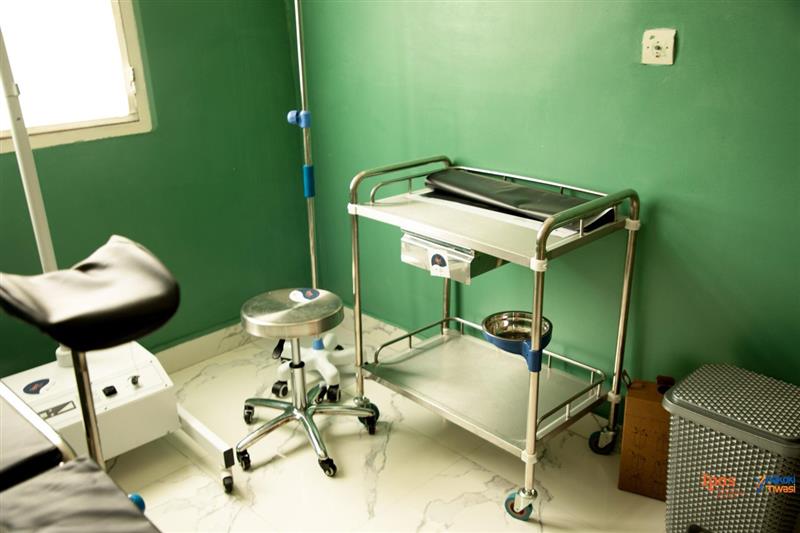
By strengthening health systems and centering women’s autonomy, Ipas DRC is contributing to lasting reductions in maternal morbidity and mortality—and ensuring that women and girls can make decisions about their bodies safely, freely, and with dignity.These centers provide safe abortion and family planning services, reducing the risks associated with unsafe practices and improving the overall quality of care for women and adolescents.

Diagnosed with a disability at a very young age, Paul Kwami grew up as the only one among seven children living with this condition. Now 25 years old, Paul serves as the president of the Association of Young People with Disabilities United for the Development of Kisenso (AJHUKAD) and works as a community health worker (RECO) in the Kisenso health zone. Each week, He conducts awareness activities across eight of the twenty‑two avenues within the REGIDESO health area—ensuring that critical information on sexual and reproductive health (SRH) reaches those who need it most.
His journey has been shaped by persistence and courage. In the beginning, he struggled with self‑stigma and doubted whether he would be accepted as a RECO, fearing how others would perceive him. Still, he chose to attend Ipas DRC’s trainings.
he shares.

Paul Kwami raising community awareness
Across the DRC, people with disabilities continue to experience significant barriers in accessing SRH services—driven by misconceptions, inaccessible information, and community stigma. Yet their leadership is essential to help women and girls understand and claim their reproductive rights, particularly in community engagement and awareness-raising.
In Kinshasa, many people with disabilities experience discrimination, especially women and girls seeking SRH services. These attitudes often stem from misinformation and harmful social norms.
Research conducted by the School of Public Health in 2024 revealed that knowledge about contraception remains low, with 50.1% of respondents believing that using a contraceptive method of her choice exposes a woman to health risks, and 70.7% think women should not access contraception without someone else’s authorization. These misconceptions highlight the urgency of community outreach and accurate SRH information for women and girls.

From left to right: the Head nurse, Paul, the Kisenso Area Coordinator, and the Ipas Community Engagement Officer in front of the REGIDESO Reference Health Center
The DRC’s 2003 ratification of the Maputo Protocol was a significant milestone. Article 14 recognizes women’s right to health—including SRH—and requires states to allow access to safe abortion in specific circumstances such as rape, incest, threats to a woman’s physical or mental health, or severe fetal anomaly.
These commitments reflect the core pillars of Ipas DRC’s work :
Expanding access to family planning and SRH services through community‑led sensitization and strong, confidential referral systems guided by RECOs ; Improving quality of care by training providers and ensuring consistent availability of essential supplies ; Centering women and girls by delivering safe, respectful, rights‑based services that uphold their autonomy and dignity.
In Kisenso—a dense and underserved municipality of Kinshasa—Ipas DRC has worked alongside local structures to strengthen the health system. This includes training RECOs, equipping health centers, supporting essential medicines, and building provider capacity. Training sessions on values clarification and attitude transformation (VCAT) have helped both providers and community actors better understand SRH rights, improve responses to gender‑based violence (GBV), and promote access to comprehensive, woman‑centered safe abortion care (SCACF).
Paul has seen this impact firsthand :
With financial support from the Swedish International Development Cooperation Agency (Sida), the REGIDESO maternity now offers a comprehensive package of SRH services—including family planning, antenatal care, GBV management, and access to safe, stigma‑free abortion. Ipas DRC has also established a secure referral circuit to ensure timely and confidential care. Two trained medical providers now offer comprehensive, woman‑centered safe abortion care.
A study by the School of Public Health shows that 68.4% of Kinshasa residents believe abortion is not authorized in the DRC, and 56.1% think women should not access safe abortion services—evidence of persistent misinformation and negative attitudes toward reproductive rights.
Despite these barriers, RECOs continue to to play a decisive role in shifting norms, informing women about family planning, and reducing risks linked to unsafe abortion. Between June and December 2025, community outreach and CAC services helped 98 women—aged 15 and above—avoid life‑threatening complications and maternal death.
This progress shows that even in contexts where stigma and misinformation remain entrenched, community‑driven change and strengthened health systems pave the way for safe, accessible, and rights‑based care.
Today, eight Ipas‑supported health facilities in Kisenso offer SRH services—ensuring that every woman and girl has equitable access, free from exclusion and stigma.


